

Organize your questions and next steps, then save your worksheet.
Summary and next steps
Cataract cost sharing depends on covered services, provider and facility billing, upgrades and your own coverage. A headline percentage is not the whole bill.
- Ask which providers and facilities will send statements.
- Confirm remaining deductible, approved amounts and secondary coverage.
- Request an itemized estimate before optional upgrades.
Editorial maintenance: October 24, 2026. Summary layout, related links and technical metadata updated. This is not a full clinical review.

Last updated: October 15, 2026.
In 2026, the standard Medicare Part B premium is $202.90/month, and the annual deductible is $283. Once you’ve hit that deductible, Part B usually covers about 80% of the Medicare-approved amount for cataract surgery. Sounds simple, right? You pay the other 20%, plus anything extra for “upgrades” or services Medicare doesn’t cover.
Turns out: a lot.
This guide explains billing questions and uses family scenarios as educational illustrations, not verified invoices or patient outcomes. No checklist or example can guarantee coverage or predict a particular bill.
In the next few minutes, you’ll learn what Medicare Part B actually covers when it comes to cataract surgery, where the seven most common cost traps are hiding (spoiler: one is in the waiting room), and how to estimate your real out-of-pocket costs in under a minute—even if all you’ve got is your parent’s Medicare card and a vague sense of panic.
If you’re feeling tired, overwhelmed, and desperately trying to protect your parent’s eyesight without blowing your own budget, trust me: you’re not alone—and you’re exactly where you need to be.
Part 1 – How Medicare Part B really pays for cataract surgery in 2026
Let’s start with the foundation: what Medicare Part B actually covers when your eye doctor says, “It’s time to take that cataract out.”
In 2026, cataract surgery is usually treated as an outpatient procedure. That means Part B, not Part A, is doing the heavy lifting. After you meet your yearly Part B deductible ($283 in 2026), Medicare generally pays 80% of the Medicare-approved amount for:
- The surgeon’s fee to remove the cataract and implant a basic intraocular lens (IOL)
- The facility costs at a hospital outpatient department or ambulatory surgery center
- Anesthesia services
- Reasonable pre-op and post-op visits related to the surgery
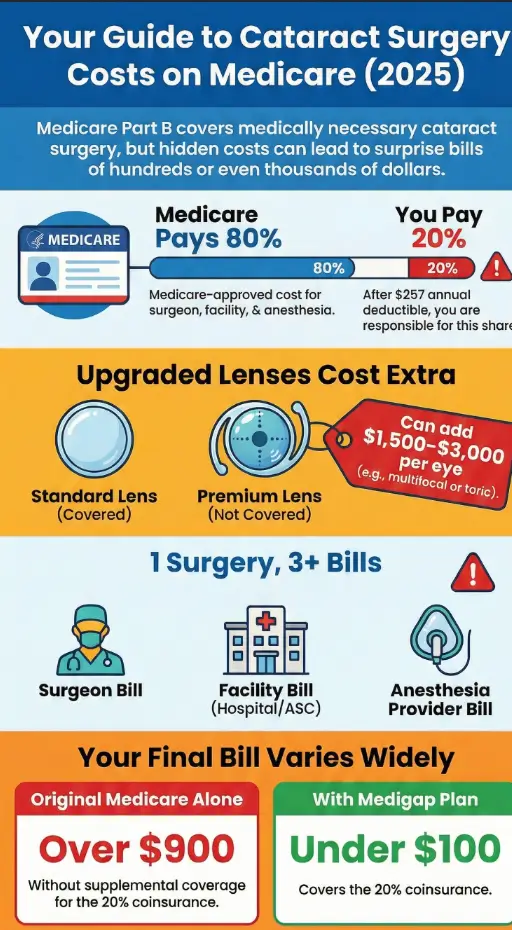
Your 20% coinsurance is based on that Medicare-approved amount, not on whatever sky-high number the sticker price says. If your provider “accepts assignment,” they agree to take the Medicare-approved amount as full payment, which protects you from big surprise markups.
One line that saved us: “Do you accept Medicare assignment for all parts of this cataract surgery, including anesthesia and the facility?”
- Confirm the provider bills under Part B as outpatient.
- Ask every entity (surgeon, facility, anesthesia) if they accept assignment.
- Write down “Part B, 80/20 after $283 deductible (2026)” on your cost sheet.
Apply in 60 seconds: Call the surgery scheduler and ask, “Is all of this billed under Medicare Part B, and do all providers accept assignment?”

The quick math: premiums, deductibles, and typical cataract surgery bills (2026, US)
Numbers first, so you can see the battlefield.
- Standard Part B premium 2026: $202.90/month for most people (higher if you’re subject to IRMAA based on income).
- Part B annual deductible 2026: $283.
- Coinsurance after deductible: You pay 20% of the Medicare-approved amount for covered services; Medicare pays 80%.
Obtain the actual approved amounts for the surgeon, facility and anesthesia. An unsupported national range is not a reliable basis for the 80/20 calculation or for comparing settings.
So, if the approved amount were $3,000 for one eye and you had already met your deductible this year, a very rough sketch looks like:
- Medicare pays about $2,400 (80%).
- You pay about $600 (20%), plus any non-covered upgrades or extra tests.
If deductible remains, apply it before the 80/20 split. For approved amount A and remaining deductible R, the covered-services illustration is min(A,R) + 20% × max(A−R,0). Adding the whole deductible on top of 20% of A overcounts the patient share.
Show me the nerdy details
Medicare-approved amounts are based on fee schedules that vary by location and type of facility. Cataract surgery itself is usually coded with CPT codes such as 66984 (routine cataract surgery with IOL) or 66982 (complex case). The facility (hospital outpatient vs. ambulatory surgery center) has its own payment rate, and the surgeon has another. Medicare then applies its fee schedule, and your 20% coinsurance is calculated on that adjusted amount, not on the pre-insurance “charge master” price. If a provider doesn’t accept assignment, they may bill up to a limited amount above the Medicare-approved level, which is why confirming assignment status is so important.
- Look for the phrase “Medicare-approved amount” on estimates.
- Ask for the CPT code and the facility type (ASC vs hospital outpatient).
- Keep 20% of that approved number in your mental budget.
Apply in 60 seconds: Call the billing office and ask, “What’s the Medicare-approved amount you expect for CPT 66984 at your facility this year?”
60-second Medicare cataract coverage check
Before we dive into horror stories, let’s confirm whether your situation is actually in cataract-surgery territory and how Part B likely sees it.
Eligibility checklist
Yes/No questions:
- Has an ophthalmologist (MD/DO) diagnosed a cataract that significantly impairs vision in daily activities (driving, reading, work)?
- Is the surgeon Medicare-enrolled and willing to bill Part B?
- Is the planned surgery outpatient (hospital outpatient or ambulatory surgery center) or in-office with appropriate equipment?
- Is the planned lens at least a standard monofocal IOL (not only a cosmetic upgrade)?
- Do you have active Medicare Part B coverage in the month of surgery?
These questions help prepare a coverage inquiry. Checking every box does not establish eligibility, medical necessity or payment; the clinician documents the actual findings and the plan applies its rules.
Ask the surgeon which services are clinically needed and eligible for coverage, and request a written estimate for any noncovered service. Do not change or invent a diagnosis to fit a benefit.
Apply in 60 seconds: Circle yes/no on each line for your situation and note the one question that feels shaky. That’s your first phone call this week. Save this table and confirm the current rules on the official Medicare site before you schedule.
Part 2 – Seven billing questions to clarify
Trap 1 – Assuming “Medicare covers everything” for cataract surgery (2026, US)
The biggest trap is psychological. “Medicare covers it” often gets translated in the brain as “I won’t owe much.” In reality, even when Medicare Part B is doing its job perfectly, you still face:
- The annual Part B deductible (up to $283 if you haven’t met any of it yet).
- 20% coinsurance on the Medicare-approved amounts.
- Potential copays or facility fees, especially in hospital outpatient settings.
How to disarm this trap: any time someone says “covered,” translate it in your notes to “Part B 80/20 after deductible; what is my estimated 20% here?”
Trap 2 – Premium lens upgrades (multifocal, toric) that Part B won’t fully cover
Medicare Part B generally covers a basic monofocal lens implant if it’s medically necessary. The moment you move into “deluxe” territory — multifocal lenses, extended-depth-of-focus lenses, advanced astigmatism correction beyond the standard — you’re entering a cost-sharing gray zone.
What often happens in the real world:
- The base cost of a standard lens and its implantation is covered under Part B.
- The “upgrade” portion (the difference between basic and premium) is billed directly to you as an out-of-pocket charge.
- The additional fee depends on the actual lens and refractive services. Obtain a written amount and coverage explanation rather than assuming a national upgrade range.
“Write down the code for the basic lens and the code for the premium lens, then ask what Medicare approves for each. Your decision may change once you see those two numbers on paper.”
Trap 3 – Pre-op tests that Part B may not see as “medically necessary”
Modern cataract surgery planning can involve a buffet of eye measurements: optical coherence tomography (OCT), corneal topography, advanced biometry, and more. Some are essential for a safe, accurate result; others are nice-to-have upgrades.
Part B generally covers tests that are medically necessary for diagnosing or treating a condition. But if your surgeon’s office has a “premium package” of extra imaging bundled with fancy lenses, those add-ons can end up in the not-covered or partly-covered column.
Illustrative question: Ask the clinician why each proposed test is needed and ask billing which services are covered. Do not decline a clinically necessary test solely because a package sounds optional.
- Ask for each test’s name and whether it’s needed for a standard lens.
- Request a separate written price for optional imaging.
- Skip bundles you don’t understand until someone explains them line by line.
Apply in 60 seconds: Email or call the office: “Can you highlight which pre-op tests are clinically needed and covered for a standard IOL and which are optional upgrades?” Save that list and confirm the current fee schedule with the provider.
Trap 4 – Facility choice (ASC vs hospital outpatient) that changes your 20%
Cataract surgery can happen in:
- An ambulatory surgery center (ASC)
- A hospital outpatient department
- Occasionally, a properly equipped office-based surgery suite
The Medicare-approved amount is often lower in ASCs than in hospital outpatient departments, which means your 20% is smaller, too. In some regions, the difference can be several hundred dollars per eye, even with Medicare paying 80% of each setting’s own approved rate.
Ask whether your medical history affects the appropriate surgical setting, then compare itemized estimates for clinically suitable options. A story about a 25% difference does not predict your local rates.
Key question: “Does my eye or medical history require a hospital outpatient setting, or is an ASC safe and available — and what’s the estimated Medicare-approved amount in each location?”
Trap 5 – Anesthesia and pathology that show up as surprise separate bills
In theory, you know anesthesia and any tissue analysis will cost something. In practice, a lot of people are still shocked when they get entirely separate bills from:
- The anesthesia group
- A pathology lab (if any lens capsule or tissue is sent)
Confirm each provider’s assignment status, the actual covered approved amount and any noncovered service. If you use a Medicare Advantage plan, check its network and benefit rules; do not treat Medigap as the same type of network plan.
Trap 6 – Post-op glasses, drops, and follow-ups that don’t feel like surgery costs (but are)
Part B covers one pair of eyeglasses with standard frames or one set of contacts after each cataract surgery that implants an IOL. Additional eyewear features and medicines have their own coverage rules. Ask the surgeon and drug plan about the prescribed drops and patient cost; do not assume a universal pharmacy price range.
We felt this one right away. The surgery itself was manageable; the sticker shock came at the pharmacy. Only after I asked the surgeon about generics and “combo” drops did we find a more affordable regimen that was still safe for her.
Pro tip: ask your surgeon for the medication plan two weeks before surgery and shop prices at multiple pharmacies (especially if you have Part D or another drug plan).
Trap 7 – Ignoring Medigap, Medicare Advantage, and IRMAA until it’s too late
Medigap benefits depend on the specific policy and eligible Original Medicare services. Medicare Advantage is a different arrangement with plan-specific copays or coinsurance, networks and authorization. Some PPO benefits may apply outside the network at a different cost; confirm your actual plan instead of assuming all plans use the same rule.
Meanwhile, higher-income retirees can be hit with IRMAA (an income-related surcharge) that increases their Part B and Part D premiums by hundreds of dollars per month, even before surgery enters the picture.
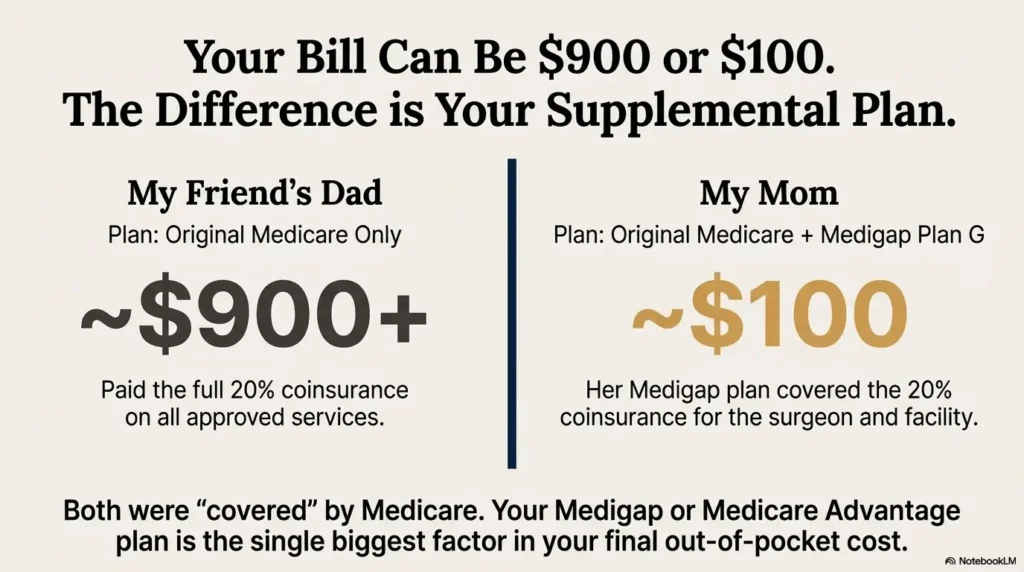
Illustrative comparison: Original Medicare, Medigap and Medicare Advantage can produce different patient responsibility. Use the actual policy benefits rather than another family’s $100 or $900 bill. Premiums, including IRMAA, are separate recurring costs and do not change the Part B coinsurance percentage for the surgery.
- Confirm if you have Original Medicare + Medigap or a Medicare Advantage HMO/PPO.
- Ask each plan how cataract surgery is coded and what your share is.
- Note any IRMAA surcharges so you’re not surprised by premium jumps.
Apply in 60 seconds: Grab your Medigap or Advantage card and call the number on the back: “What would my estimated out-of-pocket be for standard cataract surgery with an IOL this year?” Save their answer and confirm against your written fee schedule.
How Medigap, Medicare Advantage, and employer plans change your bill
This is where the “coverage tiers” mindset helps. Think of your situation as one of these five tiers:
- Original Medicare only (Part A + B): pay premium + deductible + 20% coinsurance on approved amounts.
- Original Medicare plus Medigap: confirm the exact policy’s deductible, coinsurance, copay and excess-charge benefits; plan letters are not interchangeable.
- Medicare Advantage HMO with in-network surgeon: premium (sometimes $0) + fixed copay or percentage for surgery; strict network rules.
- Medicare Advantage PPO with out-of-network surgeon: higher copay/coinsurance; more unpredictable bills.
- Original Medicare + retiree or employer coverage: complex coordination of benefits; sometimes better drug coverage.
Region matters too. In the US, Medicare rules are federal, but the actual approved amounts can differ by ZIP code and facility. A hospital outpatient department in a high-cost urban area will often carry higher approved fees than an ASC in a smaller city, even under the same Part B rules.
Coverage Arrangements: Original Medicare, Medigap and Advantage
- Tier 1 – Original Medicare only: Estimate 20% of approved amounts + deductible. Budget on the higher side.
- Tier 3 – Original + Medigap Plan G: After deductible, Medigap often pays most Part B coinsurance for covered services.
- Tier 5 – Medicare Advantage HMO in-network: Often a fixed copay per surgery, but only if using in-network providers and facilities.
Ask your insurer for a one-page explanation of cataract surgery coverage under your specific plan and year. If the answer feels vague, escalate and ask for the “benefits summary” that lists cataract surgery or outpatient surgical procedures explicitly.
Apply in 60 seconds: Circle your tier, then write a number next to it: “My estimated cataract surgery share is around $____ per eye.” Save this table and verify against your plan’s 2026 benefits booklet.
Cataract Surgery Estimate Questions by Provider
Use this as a starting point only. Real numbers depend on region, facility, and your exact coverage.
| Item | What to request | What to verify |
|---|---|---|
| Surgeon | Actual procedure and approved amount | Assignment and estimated patient share |
| Facility | Setting and separate approved amount | Clinical suitability and cost-sharing |
| Anesthesia | Provider and covered services | Assignment or plan network rules |
| Lens/refractive extras | Itemized proposed additional services | Noncovered fees and written benefits |
Example only, not a quote. Use this to frame questions for your actual providers.
Mini estimator (paper-and-pen version)
- Ask for the total Medicare-approved amount for your cataract surgery (surgeon + facility + anesthesia) per eye: A = $______
- Record remaining Part B deductible: R = $______ (0–283 for 2026).
- Apply only the amount of deductible that fits within the approved charge: D = min(A, R).
- Calculate the covered-services illustration for Original Medicare without supplemental benefits: E = D + 0.2 × max(A − D, 0). Confirm noncovered charges and specific Medigap benefits separately; this is not a Medicare Advantage formula.
Illustrative covered-services share = E. Add actual noncovered charges separately; ask the plan for the final patient estimate.
Apply in 60 seconds: Plug in approximate numbers from your estimates using this formula. Save it, then confirm each line with your provider’s billing office and your insurance plan.
Part 3 – Scripts, checklists, and phone calls to make before surgery
At this point, you know the structure: premium, deductible, 80/20 coinsurance, and the seven traps. Now we turn that into a short list of conversations you can actually have this week.
Script 1 – Calling the surgeon’s office
You: “Hi, my name is _____. I’m calling about my (or my mom’s) upcoming cataract surgery. Can I ask a few questions about how this is billed under Medicare Part B?”
Questions to ask:
- “Is the surgery billed as outpatient under Medicare Part B?”
- “Do the surgeon and facility both accept Medicare assignment?”
- “Can you share the expected Medicare-approved amount for this surgery this year?”
- “Which pre-op tests are clinically needed and covered, and which are optional extras?”
- “Is any part of this a premium or deluxe lens upgrade? If so, what is that portion’s exact cost?”
Script 2 – Calling your Medigap or Medicare Advantage plan
You: “Hi, I have a question about how cataract surgery is covered this year.”
Questions to ask:
- “I have Medicare and [Plan Name]. For standard cataract surgery with an IOL, what is my expected out-of-pocket per eye?”
- “Is it a flat copay or a percentage? What’s the limit?”
- “Does the surgeon and facility I’m using count as in-network?”
- “Do you cover the 20% coinsurance after Medicare for surgeon, facility, and anesthesia?”
- “Does my plan include any extra vision benefits or discounts for glasses after surgery?”
Quote-prep list
Before you start calling, gather:
- Medicare card (red, white, and blue)
- Medigap or Medicare Advantage card
- List of medications and diagnoses (especially diabetes, glaucoma, macular degeneration)
- Proposed surgery date and eye (right vs left)
- Surgeon name, facility name, and any CPT codes they provided (like 66984)
Apply in 60 seconds: Drop these five items into a folder or notes app titled “Cataract Surgery 2026.” It will save you 20–30 minutes of shuffling during phone calls.
Infographic – your cataract surgery money map in one glance
Cataract Surgery Money Map (2026, US)
1. Before surgery
- Confirm diagnosis + medical necessity.
- Check Part B status, deductible left.
- Choose facility (ASC vs hospital outpatient).
- Verify Medigap/Advantage coverage.
2. Day of surgery
- Standard vs premium lens decision.
- Know who will bill you (surgeon, facility, anesthesia).
- Keep a simple cost sheet in your bag.
3. After surgery
- Fill drops at best-price pharmacy.
- Order Medicare-covered glasses (1 pair).
- Match each bill to your estimates.
- Appeal anything that doesn’t match codes.
Use this map as a one-page dashboard: print it or screenshot it, then write your own numbers in the empty spaces.
FAQ
1. Does Medicare Part B fully cover cataract surgery?
No. In 2026, Part B generally covers 80% of the Medicare-approved amount for medically necessary cataract surgery after you’ve paid the annual Part B deductible ($283). You’re responsible for the remaining 20% coinsurance and any non-covered extras like premium lenses or optional tests. A Medigap plan may cover some or all of that 20%, depending on the plan.
60-second action: Call your plan and ask, “For standard cataract surgery in 2026, what is my estimated out-of-pocket per eye?”
2. How much will cataract surgery cost me out-of-pocket with Original Medicare only?
For covered Original Medicare amounts, apply the remaining deductible first and then 20% coinsurance to the balance. Actual approved amounts, uncovered services and secondary benefits determine payment; no low-to-mid-hundreds range applies to every patient.
60-second action: Use the actual approved amounts and confirm the estimate with billing.
60-second action: Use the mini estimator above with the real approved amounts from your surgeon’s office.
3. Does Medicare pay for glasses after cataract surgery?
Part B covers one pair of eyeglasses with standard frames or one set of contact lenses after each surgery that implants an IOL. Ask the supplier and plan about cost-sharing, assignment and any additional eyewear features. Medigap and Medicare Advantage benefits differ.
60-second action: Confirm the supplier and expected patient responsibility before ordering.
60-second action: Before surgery, ask your plan, “Where should I go to get my post-cataract glasses, and what will I pay?”
4. What if I can’t afford the coinsurance for cataract surgery?
If the 20% share is too high, start by asking the provider’s billing office whether they offer payment plans. If your income is limited, you may qualify for a Medicare Savings Program or Medicaid, which can help pay premiums and cost-sharing for Medicare. Some nonprofit hospitals and clinics have financial assistance or charity care policies, even for insured patients.
60-second action: Call your state’s SHIP (State Health Insurance Assistance Program) and say, “I’m struggling with cataract surgery costs. What programs can help cover Medicare premiums and cost-sharing?”
5. What happens if my cataract surgery claim is denied by Medicare?
If a claim is denied, read the reason and appeal instructions on the Medicare Summary Notice or plan decision. Original Medicare’s first appeal is a redetermination; follow the notice’s filing deadline and ask the provider for supporting records. Medicare Advantage has its own plan appeal process. See official appeal guidance.
60-second action: If you receive a denial notice, highlight the reason code, then call the surgeon’s billing office and ask, “Can you walk me through how we appeal this specific denial together?”
Optional video: Open the video on YouTube (external site).
Final 15-minute checklist before you book the surgery
Once we slowed down and treated cataract surgery as both a medical decision and a small financial project, everything felt lighter. The same Medicare rules that first looked impossible turned out to be fairly predictable once we knew which questions to ask and which traps to sidestep.
- ✅ Confirm medical necessity and that your surgeon and facility accept Medicare assignment.
- ✅ Get written estimates that include Medicare-approved amounts and your estimated share.
- ✅ Decide in advance whether premium lens upgrades are worth the full, out-of-pocket cost.
- ✅ Use the mini estimator to sanity-check every bill that arrives.
- ✅ Keep that money map infographic handy so you always know where you are in the process.
- Lock in this year’s deductible and coinsurance pattern.
- Compare coverage tiers before you agree to upgrades.
- Match every bill back to a code, an estimate, and a plan.
Apply in 60 seconds: Pick one phone call — surgeon, plan, or pharmacy — and make it today. Capture their answers in your “Cataract Surgery 2026” folder so the rest of the process feels like following a checklist, not dodging surprises.
Review note: 2026 premiums and deductibles, the cost-sharing formula, plan distinctions and appeal guidance were checked. Sources: Medicare costs, cataract coverage, and Original Medicare appeals.
Medicare costs and plan benefits can change. Confirm the amounts for the actual year of surgery and the patient’s specific coverage before relying on an estimate.
Keep the itemized estimate, coverage explanation and any appeal instructions with the surgery records.
PUT THIS GUIDE TO WORK · INTERACTIVE WORKSHEET
Plan one confirmed cataract service cost
Use this worksheet alongside the article: Cataract Surgery and Medicare Part B: Coverage and Cost-Sharing Questions. Use the fields provided to organize your notes and next actions, then save your worksheet.
Your entries stay in this page and are cleared when you reload. No account is needed. Saved files are downloaded only to your device.
This worksheet does not establish coverage or eligibility. Use the Part B model only after the provider confirms a covered service and accepts assignment. It uses deductible applied + 20% of the remaining approved amount + extra charges. Medigap, Medicaid, other insurance, facility charges, excess charges, and plan-specific rules are not modeled. A plan quote is entered directly rather than applying the Part B formula.
Verify Medicare’s current costs and assignment rules · Worksheet rules checked October 20, 2026.
How to use your result
Save the worksheet before leaving this page. Recheck any quote, date, or instruction with the relevant provider, pharmacist, manufacturer, or official organization. A completed checklist means you recorded the steps, not that an outcome is guaranteed.
Worksheet added October 20, 2026. Read the article above for context and its stated review scope.