

Organize your questions and next steps, then save your worksheet.
Summary and next steps
Ask the surgical and diabetes teams to coordinate retinal assessment, medicine instructions and follow-up. An online readiness checklist cannot clear you for surgery.
- Ask what retinal findings matter before the operation.
- Get individual diabetes-medicine and preparation instructions.
- Confirm postoperative retinal and surgical follow-up.
Editorial maintenance: October 24, 2026. Summary layout, related links and technical metadata updated. This is not a full clinical review.

Cataract surgery for diabetics calls for extra planning around retinal health, glucose management, and recovery. Diabetes can increase the risk of retinal swelling and limit the vision gained from removing a cataract. The patient-style examples below are illustrative, not verified personal medical histories.
This guide covers the main risks, questions for your surgical and diabetes teams, and nine preparation gaps to discuss before surgery. Use the checklists and cost questions to prepare for an individualized plan; they cannot determine whether you are ready for surgery.
Why cataract surgery feels different when you have diabetes
For most people, cataract surgery gets pitched as a quick, almost routine tune-up: in and out, tiny incision, shiny new lens, back to life. That story is mostly true—unless you add diabetes.
People with diabetes are more likely to develop cataracts, to develop them younger, and to watch them progress faster than their friends without diabetes. That means many of us hit the operating room while we’re still working, driving, caring for kids—or parents. The stakes feel higher.
And underneath the cloudy lens, there’s the retina: fragile blood vessels, maybe early diabetic retinopathy, maybe tiny leaks in the macula. That’s the part that turns a “simple” lens swap into a more delicate balancing act. Diabetic eye disease—especially diabetic retinopathy and diabetic macular edema—is one of the leading causes of preventable blindness in adults.
Cataract surgery can improve vision when a cloudy lens affects daily life, but the expected benefit depends on your retina and other eye conditions. Ask your surgeon to explain the likely benefit and risks for your own eye.
Think of this as your “translator” between surgical optimism and diabetic reality.

60-second diabetic cataract surgery readiness check
Before we dive into the scary (and fixable) details, run this quick self-check. It’s not a medical verdict—just a reality snapshot you can bring to your next visit.
Questions to resolve before surgery
Answer each with a simple “Yes/No/Not sure”.
- My surgeon has assessed my retina recently enough for this operation and explained whether further examination or imaging is needed.
- Someone has told me clearly whether I do or do not have diabetic retinopathy.
- I know my latest HbA1c and fasting/post-meal glucose pattern from the last 3 months.
- My diabetes team has weighed in on whether this is a good time for elective surgery.
- I understand whether my macula is dry, swollen, or at risk for edema.
- I have a written estimate of cataract surgery cost, including lenses and follow-up.
- I have a written fasting and medication plan well before surgery, including any hold and restart instructions for insulin, GLP-1 medicines, SGLT2 medicines, and other drugs. I will not change them on my own.
- I have someone to drive me home and stay reachable the first 24 hours.
- I know who to call after hours if my eye suddenly hurts or vision drops.
Any unresolved question about fasting, medicines, retinal disease, or urgent symptoms deserves clarification before surgery. This checklist is not a score or medical clearance.
Save this checklist and confirm each point with your own eye team before scheduling surgery.
Extra risks of cataract surgery when you have diabetes
Let’s name the elephant in the operating room: yes, cataract surgery is generally safe, but diabetes adds some specific risks your surgeon and retina specialist will be watching for.
1. Higher risk of macular edema (retinal swelling)
Inflammation after cataract surgery can cause pseudophakic cystoid macular edema (CME). People with diabetes may also have pre-existing or worsening diabetic macular edema (DME). These can overlap, but they are not the same diagnosis; examination and OCT imaging help the eye team identify the cause and appropriate treatment.
A retrospective study of people with diabetes found an association between higher HbA1c and postoperative CME. An association does not establish a universal HbA1c cutoff or predict an individual outcome. Agree on safe glucose targets with your diabetes and surgical teams.
2. Possible progression of diabetic retinopathy
Existing diabetic retinopathy or macular edema may affect surgical timing, visual recovery, and follow-up. Ask whether retinal treatment is needed before or after surgery. Injections or laser are used for specific clinical indications, not automatically for everyone with diabetes.
3. Slower healing and slightly higher infection risk
Poorly controlled blood sugar can slow wound healing and increase the risk of infection in many surgeries, including eye surgery. The eye incision is tiny, but it still needs a clean, well-fed body to heal. Good perioperative control is less about achieving perfection and more about avoiding big, chaotic swings in glucose during the healing window.
4. Glare, halos, and “vision disappointment”
If the retina isn’t healthy, a perfect new lens can still deliver imperfect vision. Some diabetics feel underwhelmed after surgery because retinopathy, DME, or nerve damage limits the sharpness they can achieve—even when the cataract is gone. Managing expectations is part of protecting your mental health around surgery.
- Ask directly about your risk of macular edema and retinopathy progression.
- Ask which retinal examinations or imaging are needed before and after your operation.
- Follow clinician-agreed glucose targets and medication instructions; avoid rapid self-directed changes.
Apply in 60 seconds: Write down one question about macular edema and one about retinopathy to ask at your very next visit.
Questions to ask your cataract surgeon when you live with diabetes
This is the part where we turn vague dread into concrete, answerable questions. Print these, screenshot them, or copy them into your notes app. You won’t remember them all in the waiting room.
1. “How healthy is my retina right now?”
- Do I have diabetic retinopathy? If yes, what stage?
- Is there any sign of macular edema or previous bleeding?
- Should I see a retina specialist before surgery?
2. “What is my personal risk of macular edema after surgery?”
- Do we need extra anti-inflammatory eye drops or injections to protect the macula?
- Will you use OCT (retinal scan) before and after surgery to monitor swelling?
3. “Is this the right time, given my diabetes control?”
- Given my HbA1c and glucose pattern, would you recommend we stabilize control first?
- Are there diabetes-related reasons to delay or not delay surgery?
4. “How will you coordinate with my diabetes team?”
- Can I have written medicine and fasting instructions well in advance, including when any medicine must be held and restarted?
- Who decides adjustments—your team or my endocrinologist/primary care doctor?
5. “What lens options are actually worth paying for in my situation?”
- Given my retina health, would a premium multifocal or toric lens actually help, or could it worsen glare?
- What are the coverage tiers and premium lens upgrades—what’s standard, and what counts as an upgrade, with extra premium and out-of-pocket costs?
6. “What will I realistically see—and when?”
- How quickly should I expect usable vision for driving, reading, and screens?
- What symptoms are normal in the first weeks, and which are a red flag?
7. “Who do I call at 10 p.m. if something feels wrong?”
- Is there a 24-hour number for sudden pain, flashes, or dark shadows?
- What’s the emergency plan if my blood sugar crashes or spikes around surgery?
Take these questions, add your own money questions, and reframe the visit: you are interviewing the surgery team, not the other way around.
9 preparation gaps to discuss before cataract surgery
These nine examples highlight preparation gaps to discuss with your own team. They do not describe a verified patient’s treatment or outcomes.
1. Treating cataract surgery like a quick errand
I almost treated the procedure like a dental cleaning—pick a date, show up, done. The reality? For diabetics, it’s more like planning a small project: pre-op labs, retina imaging, medication adjustments, rides, time off work, and a follow-up schedule.
Better move: Put surgery and follow-up dates on a calendar and block out your first 48–72 hours after each eye. Protect the time the way you’d protect an important work deadline.
2. Going in with “mystery” blood sugar
At one point, my plan was, “I’ll just do my best that week.” That’s not a plan; that’s vibes. Studies show that poorer pre-op glycemic control is associated with higher risk of post-cataract macular edema.
Better move: Aim for a calm, boring glucose pattern in the weeks before surgery, not a crash diet of strict control. Bring your last 2–4 weeks of readings (or CGM download) to pre-op so the team can see your usual pattern, not your best day.
3. Ignoring the retina because “the cataract is the main problem”
At first I was so focused on fixing the cloudy lens that I barely asked about the retina underneath. That’s like renovating a house without checking if the foundation is cracked.
Better move: Ask specifically: “Is my retina healthy enough that a new lens will actually deliver good vision? Do we need to treat retinopathy or edema before surgery?” In some cases, retina treatment first can dramatically improve your odds of a clear result.
4. Assuming all lenses are created equal—for all eyes
The brochure made every intraocular lens sound magical. But in diabetics, especially with retinopathy or macular changes, some “premium” lenses don’t play nicely with contrast or night vision.
Better move: Ask, “If this were your eye, with this retina and this level of diabetes, which lens would you choose and why?” Expensive is not the same as appropriate.
5. Not asking for a real cost breakdown
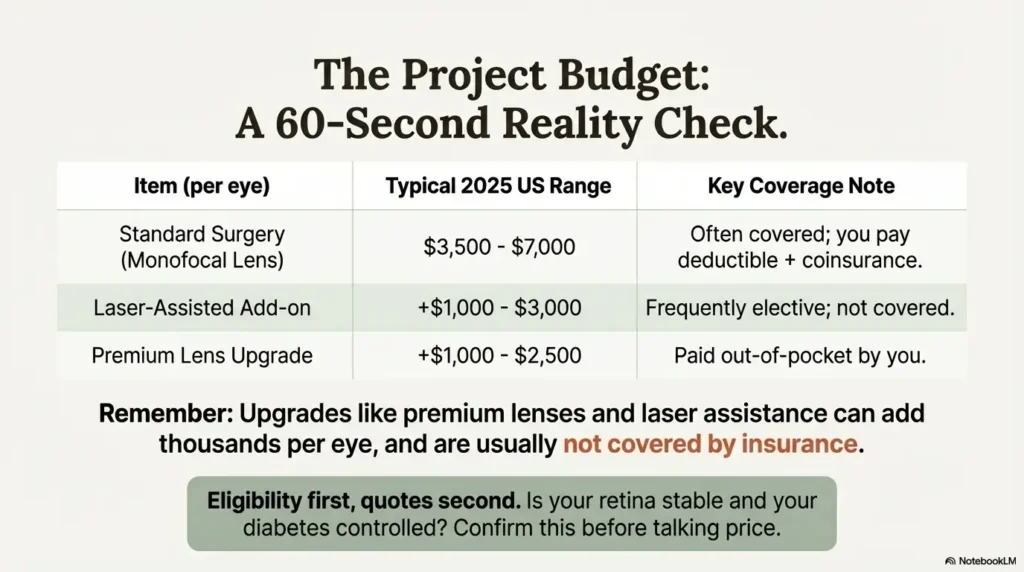
I almost signed the consent form without a written estimate that separated standard coverage vs. upgrades, deductibles, and out-of-pocket costs. In many places, standard monofocal cataract surgery is covered by insurance or public systems, but laser-assisted surgery and premium lenses can add thousands per eye.
Better move: Ask for a line-item estimate: surgeon fee, facility fee, anesthesia, lens type, post-op visits, and any separate retina imaging. Treat it like any other major purchase.
6. Forgetting that anesthesia and fasting rules interact with diabetes
Generic fasting instructions may conflict with an individual diabetes regimen. Ask the surgical and diabetes teams to reconcile the plan before the procedure.
Better move: Get a written plan early enough to cover medicines that may need changes before the day of surgery, as well as fasting, glucose monitoring, low-glucose treatment, and restarting medicines. Do not use generic advice to change doses yourself.
7. Underestimating recovery time—and screen time
I pictured myself back on a laptop in 24 hours. Instead, my eye felt gritty, my focus changed from hour to hour, and bright screens were exhausting.
Better move: Expect a few days of fuzzy, “soft-focus” vision and plan lighter duties if you work on screens all day. Give yourself permission to be slightly slower and more cautious, especially with stairs and night driving.
8. Not planning for “what if something goes wrong?”
Everyone reassured me that complications were rare (true), but no one pushed me to plan for them (less ideal). For diabetics, retinal swelling, pressure spikes, or infections—even if rare—can be more serious.
Better move: Before surgery, ask: “If I develop macular edema or a pressure spike, what’s our plan? Do you treat it here or refer me?” Knowing the next step makes it less terrifying if you need it.
9. Assuming one surgery fixes all vision problems forever
Cataract surgery can dramatically improve clarity, but it doesn’t “cure” diabetic eye disease. Retinopathy, glaucoma risk, and macular changes still need lifelong monitoring.
Better move: Treat the surgery as a chapter, not the whole book. Ask your team how often you should have dilated exams and retinal imaging after surgery, given your diabetes duration and control.
Costs, coverage, and written estimates (US)
Now for the uncomfortable part: money. Cataract surgery is one of the most commonly performed operations in the world—and in the United States, it’s also a significant business.
There is no single reliable price for your operation. Under Original Medicare, eligible cataract surgery generally involves the remaining Part B deductible and 20% of Medicare-approved amounts for covered services. Facility, surgeon, anesthesia, separate retinal care, supplemental coverage, and noncovered upgrades can change what you pay. Ask for an itemized estimate and confirm benefits with your insurer.
And remember: you may also face costs for pre-op retina imaging, extra follow-up visits, and additional treatments if diabetic macular edema appears later.
Written estimate: charges to check
| Item | Ask the clinic | Confirm with your insurer |
|---|---|---|
| Standard surgery and conventional lens | Separate surgeon, facility, and anesthesia amounts | Approved amounts, deductible, coinsurance, and network or assignment status |
| Optional lens or technology services | Which services are optional, and their separate prices | Which parts, if any, are covered |
| Retinal imaging or treatment | Whether billed separately before or after surgery | Medical coverage and patient cost sharing |
| Follow-up | What is included and what may cost extra | Any additional visit or treatment charges |
These are questions for your own quote, not national price averages. Original Medicare has no annual out-of-pocket maximum for medical services; Medicare Advantage and supplemental coverage have different terms.
Save this table and confirm the current fee on your provider’s official fee schedule or written estimate.
Coinsurance-only illustration
Coinsurance-only illustration: Assumes the deductible has already been met. This is not a total out-of-pocket estimate or confirmation of coverage.
Use approved amounts for covered services, not a billed or cash price. Confirm the actual patient total with your provider and insurer.
Eligibility first, quotes second. Before chasing “cheapest surgery,” confirm the basics: is your retina stable, is your diabetes reasonably controlled, and is your surgeon comfortable managing higher-risk eyes?
Details to collect before requesting a quote
Have these in front of you before you request insurance quotes or clinic estimates:
- Your diabetes type, duration, and latest HbA1c.
- Whether you have diabetic retinopathy or macular edema documented.
- Whether you need surgery in one eye or both in the next 12–18 months.
- Your remaining deductible and any plan-specific medical out-of-pocket limit. Original Medicare has no annual medical out-of-pocket maximum.
- Whether you’re considering any premium lenses or laser add-ons.
- For Medicare: which Part (A/B/C/D) you have and any Medigap plan.
Save this list and confirm each number against your insurer’s official plan documents or a benefits specialist.
Recovery, retina care, and long-term diabetes control
Once the surgery is over, the real test begins: how well your eye heals, how your retina behaves, and how your diabetes behaves around all of that.
Illustrative example: new distortion after surgery
For example, imagine noticing a new bend in straight lines two weeks after surgery. Even if the operation seemed successful, new distortion deserves a prompt call to the surgical team; do not wait for the next routine check.
The team may examine the retina and use OCT to look for swelling or other causes. Treatment depends on the findings; an illustrative example cannot predict which drops, injections, or recovery time another patient will need. Sudden vision loss, severe pain, new flashes or floaters, or a curtain over vision require immediate eye care.
How often should I be checked after cataract surgery with diabetes?
Ask for a written follow-up schedule and after-hours contact plan. The frequency of appointments and OCT scans depends on your operation, retinal findings, and recovery; diabetes does not create one universal schedule.
- Attend postoperative checks on the dates your surgical team specifies.
- Ask whether retinopathy or macular edema requires additional retina visits or OCT imaging.
- Ongoing annual or more frequent dilated exams based on your diabetes duration and control.
Guidelines for diabetic retinopathy emphasize more frequent ophthalmology visits when retinopathy is progressing or when major events—like surgery—could change the disease course.
Infographic – The three phases of diabetic cataract surgery care
Phase 1 – Before surgery
- Confirm retina status (retinopathy, macular edema).
- Stabilize glucose pattern over several weeks.
- Clarify lens choice, coverage tiers, and fee schedule.
- Coordinate with diabetes team on medication plan.
Phase 2 – Day of surgery
- Follow fasting + medication instructions exactly.
- Bring glucose meter or CGM, rescue carbs if allowed.
- Confirm ride home and 24-hour support person.
- Ask what symptoms should trigger a same-day call.
Phase 3 – After surgery
- Use drops exactly as prescribed; don’t “taper freestyle.”
- Watch for distortion, new floaters, or dark curtains.
- Keep glucose steady; avoid extreme highs/lows.
- Attend all retina follow-ups, even if you feel fine.
- Follow your individualized surgical and retinal follow-up schedule.
- Use new vision as motivation to keep long-term glucose in range.
- Report subtle vision changes early; don’t wait for dramatic loss.
Apply in 60 seconds: Add your next 3 eye appointments (or reminders to schedule them) to your calendar now.
If you’re having cataract surgery with diabetes in Korea
If you live in Korea, there’s an extra layer to all of this: how cataract surgery fits into the National Health Insurance Service (NHIS) and private health insurance (PHI).
If you are arranging surgery in Korea, request an itemized estimate in won identifying services proposed for NHIS billing and any noncovered lens or technology charges. Confirm your own eligibility and private-policy benefits directly; coverage and reimbursement cannot be inferred from this guide.
Ask the surgeon to explain the clinical reasons for the proposed timing, including your retina and macula findings. Make the timing decision on expected benefits and risks, alongside an accurate explanation of costs.
Practical questions to ask in Korea (or similar NHIS-style systems):
- “Is this surgery being billed primarily through NHIS, my private policy, or both?”
- “What’s my expected NHIS copayment in won, and what are my private insurance deductibles?”
- “Would you make the same recommendation if I had NHIS only and no private coverage?”
- “Given my diabetes and retina status, what is the risk of waiting 6–12 months vs. operating now?”
Remember: coverage doesn’t automatically mean medical necessity. You’re allowed to ask whether the timing and technique are truly in your best interest, not just covered by your plan.
Nerdy risk–benefit deep dive (optional)
Show me the nerdy details
For the curious (or anxious), here’s a simplified version of what’s going on under the hood.
Why diabetics get more cataracts: Chronic high glucose can alter lens proteins and increase oxidative stress, making the lens cloudier, earlier. Longer diabetes duration is linked to higher rates of cataract and cataract surgery.
Why retinopathy can worsen after surgery: Cataract surgery increases intraocular inflammation and can temporarily disrupt the blood–retina barrier. In eyes with diabetic retinopathy, those vessels are already fragile, so postoperative leakage and progression risk rises—especially if baseline control is poor.
Why macular edema is such a big deal: The macula is the part of the retina that handles fine detail and reading. When fluid leaks into it—whether as classic cystoid macular edema or diabetic macular edema—vision can look blurry, wavy, or washed out. Anti-inflammatory drops, steroid injections, or anti-VEGF injections may be used to treat it, depending on the pattern and severity.
Why your surgeon might add “extra” drops: Some guidelines recommend combining steroid and NSAID eye drops in diabetics, even without visible retinopathy, to reduce the risk of cystoid macular edema after surgery.
None of this means cataract surgery is unsafe for diabetics. It means you and your team are piloting a more complex flight plan—and need clearer instruments and better communication.

FAQ
Is cataract surgery safe if I have diabetes?
For most people with diabetes, yes—cataract surgery is still considered safe and can significantly improve vision. The key differences are extra attention to your retina status, tighter monitoring for macular edema, and more deliberate glucose management before and after surgery. Your 60-second action: ask your ophthalmologist directly, “Given my diabetes and retina status, do you see any special risks or extra steps we should take?”
Will cataract surgery fix my blurry vision from diabetic retinopathy?
Not necessarily. Cataract surgery replaces the cloudy lens at the front of the eye, but it doesn’t repair retina damage. If diabetic retinopathy or macular edema is causing blurriness, you may need separate retina treatments (like anti-VEGF injections or laser) before or after surgery. Your 60-second action: ask, “How much improvement is realistic from cataract surgery given the retinal findings, and what uncertainty remains?”
How much does cataract surgery usually cost if I’m on Medicare in the US?
Medicare covers eligible cataract surgery, generally with the remaining Part B deductible and 20% of approved amounts under Original Medicare. Optional upgrades, additional services, and supplemental coverage can change your total. Ask for the combined surgeon, facility, anesthesia, and other applicable patient charges; a national average cannot establish your bill.
How long should I plan to be off work after cataract surgery with diabetes?
Many people return to light work within a few days, but diabetics may want a bit more margin—especially if your job involves screens, driving, or heavy lifting. Expect a few days of visual fluctuation and fatigue. Your 60-second action: look at your work calendar and block 2–5 lighter days after each eye, with no critical deadlines or night driving.
What symptoms after surgery are an emergency?
Call your surgeon or emergency line immediately if you notice severe eye pain, sudden vision loss, a dark curtain, many new floaters, or flashes of light. These can signal infection, retinal detachment, or serious pressure spikes—conditions where hours matter. Your 60-second action: save your clinic’s 24-hour number in your phone under “Eye Emergency” and share it with your support person.
Can I ever avoid cataract surgery if I have diabetes?
Sometimes mild cataracts can be managed for a while with updated glasses, glare control, and good diabetic eye care. But once cataracts interfere with daily tasks—driving, reading, safe walking—surgery is usually the only way to restore clear vision. Your 60-second action: ask your doctor, “If I delay surgery 6–12 months, what do you realistically expect to happen to my vision and retina?”
Optional video: Open the video on YouTube (external site).
Conclusion: your next 15 minutes
Cataract surgery for diabetics is not a simple “yes/no” question; it’s a series of small, navigable decisions. The surgery itself is measured in minutes. The impact on your vision—and your life—is measured in years.
If you do nothing else today, use the clarity you have right now to make life easier for your future self:
- Book (or confirm) a dilated eye exam that includes a retina check.
- Write down your latest HbA1c and a week of glucose readings.
- Turn one of the nine preparation gaps into a direct question for your surgeon.
- Start a simple “eye folder” (paper or digital) with estimates, instructions, and your own notes.
You don’t have to become an eye expert. You just have to become the quiet project manager of your own surgery—steady, curious, and willing to ask for clear explanations.
- Questions turn vague fear into clear decisions.
- Clear decisions protect both vision and money.
- Protected vision makes every other diabetes decision easier.
Apply in 60 seconds: Choose a date for surgery—or for a second opinion—and put it on the calendar with one note: “Bring questions.”
Updated October 15, 2026. Reviewed medication-planning advice, postoperative swelling terminology, follow-up guidance, and Medicare cost information. Sources: National Eye Institute, Medicare, and the published observational study. This educational guide does not replace an individualized plan from your eye-care and diabetes teams.
PUT THIS GUIDE TO WORK · INTERACTIVE WORKSHEET
Prepare diabetes-and-cataract coordination questions
Use this worksheet alongside the article: Cataract Surgery for Diabetics: 9 Preparation Gaps and Questions to Ask. Use the fields provided to organize your notes and next actions, then save your worksheet.
Your entries stay in this page and are cleared when you reload. No account is needed. Saved files are downloaded only to your device.
This card organizes a discussion or task. It does not provide diagnosis, treatment, medication timing, driving clearance, or professional approval. Copy clinical instructions exactly and ask the professional about uncertainty.
How to use your result
Save the worksheet before leaving this page. Recheck any quote, date, or instruction with the relevant provider, pharmacist, manufacturer, or official organization. A completed checklist means you recorded the steps, not that an outcome is guaranteed.
Worksheet added October 20, 2026. Read the article above for context and its stated review scope.